Suicide Prevention: Recognizing the Signs, Starting the Conversation, and Choosing Hope

Written by Jametta Anietie Ukpong

Suicide is a serious public health concern that affects individuals, families, churches, workplaces, and entire communities. When a person dies by suicide, the effects extend far beyond the individual, leaving family members, friends, colleagues, and communities to cope with grief, unanswered questions, and often a profound sense of loss.

But suicide is preventable.

Recognizing warning signs, knowing how to respond, creating supportive environments, and helping people access appropriate care can make a meaningful difference.

I remember one Sunday during a church service when the usual flow of the service was paused because a member watching online commented that they were feeling depressed and wished they could end their life. At that very moment, the church did not ignore the message or continue with the service as usual. The congregation was informed, and everyone was encouraged to pray for the individual, asking God to strengthen, comfort, and preserve their life.

This experience reminded me that suicide prevention can begin with simply paying attention and taking someone’s words seriously.

For Christian communities, suicide prevention also means creating safe spaces where people can speak honestly about their struggles without fear of judgment or shame. It means reminding people that they are loved, valued, and not alone, while also encouraging them to seek appropriate professional and pastoral support when needed.

What Is Suicide?

Suicide refers to death caused by intentional self-directed actions with the intention of ending one’s life.

It is important to understand that suicide does not have one single cause. People may experience suicidal thoughts or behaviors for many different and often overlapping reasons, including depression and other mental health conditions, trauma, loss, relationship difficulties, financial or social stress, chronic pain, substance use, feelings of isolation, or overwhelming circumstances.

Hopelessness and unbearable emotional pain can be important risk factors, but they do not explain every suicide.

A person experiencing suicidal thoughts may feel that their circumstances will never improve or that death is the only way to escape their suffering. This is why compassionate intervention matters. A suicidal crisis can change, and people can recover with appropriate support and treatment.

Understanding Suicide: What Increases Risk?

Suicide risk can increase when several difficult circumstances occur at the same time.

Some risk factors include:

  • Depression and other mental health conditions
  • Previous suicide attempts or suicidal behavior
  • Substance or alcohol misuse
  • Experiences of trauma or abuse
  • Major relationship problems or loss
  • Social isolation or loneliness
  • Financial or employment difficulties
  • Chronic physical pain or serious illness
  • Exposure to another person’s suicide
  • Feelings of hopelessness, shame, or being trapped
  • Access to lethal means

Having one or more of these factors does not mean that someone will attempt suicide. Risk should be understood in the context of the person’s circumstances, behavior, and current mental state.

Warning Signs of Suicide

Sometimes a person may directly tell you that they are thinking about suicide. Other times, changes in their words, behavior, or mood may indicate that they are struggling.

1. Talking About Suicide or Death

Take statements about suicide seriously, even if they are made casually or indirectly.

Examples include talking about:

  • Killing themselves
  • Wanting to die
  • Having no reason to live
  • Feeling like a burden to others
  • Feeling trapped
  • Experiencing unbearable emotional or physical pain
  • Believing that things will never get better
  • Saying that other people would be better off without them

2. Changes in Behavior

Possible behavioral warning signs include:

  • Looking for ways to die or researching suicide
  • Increased alcohol or drug use
  • Acting recklessly or taking unusual risks
  • Withdrawing from activities they previously enjoyed
  • Isolating themselves from family and friends
  • Significant changes in sleeping patterns
  • Giving away important possessions
  • Saying goodbye to people in an unusual or final-sounding way
  • Sudden changes in behavior after a period of severe distress

A sudden improvement in mood after a period of intense suicidal distress should also be taken seriously, particularly if other warning signs are present.

3. Changes in Mood

Mood changes can include:

  • Depression or persistent sadness
  • Loss of interest or pleasure
  • Anxiety
  • Irritability
  • Anger or rage
  • Feelings of humiliation or shame
  • Severe emotional distress
  • Feelings of hopelessness or worthlessness

Not everyone who experiences these symptoms is suicidal. However, significant changes—especially when several occur together—deserve attention.

Don’t Ignore the Signs

One of the most important principles of suicide prevention is taking warning signs seriously.

You do not need to be a mental health professional to ask someone whether they are thinking about suicide.

In fact, asking directly can open the door to a conversation that might otherwise never happen.

You will not “put the idea” of suicide into someone’s mind simply by asking about it. A direct, calm, compassionate question can help someone feel seen and give them an opportunity to talk about what they are experiencing.

How to Start a Conversation About Suicide

You do not need perfect words.

You can begin with something simple:

“I’ve really been feeling concerned about you lately.”

“I’ve noticed some differences in you recently, and I’m wondering how you’re doing.”

“You haven’t seemed like yourself lately, and I wanted to check in.”

If you are concerned that someone may be suicidal, you can ask directly:

“Are you thinking about suicide?”

Or:

“Have you been thinking about killing yourself?”

If they say yes, don’t panic. Stay calm and continue listening.

You can ask:

  • “When did you begin feeling this way?”
  • “Did something happen that made you start feeling this way?”
  • “Have you thought about how you would hurt yourself?”
  • “Are you in immediate danger right now?”
  • “Is there anything I can do to help you stay safe?”
  • “Who else can we involve to support you?”

If there is immediate danger, do not leave the person alone. Help them connect with emergency or professional support and, when appropriate, reduce access to lethal means.

What To Do When Someone Tells You They Are Suicidal

DO:

1. Be present.
Let the person know that you care and that they do not have to face the situation alone.

2. Listen.
Give them room to express what they are experiencing without immediately trying to fix everything.

3. Stay calm.
Your reaction can influence whether they feel safe enough to continue talking.

4. Be compassionate and non-judgmental.
You may not fully understand their experience, but you can still acknowledge their pain.

5. Take them seriously.
Never assume that someone is “just seeking attention.”

6. Encourage professional help.
A doctor, psychologist, psychiatrist, counselor, crisis service, or emergency department can provide appropriate support.

7. Involve trusted people.
If someone’s life may be in danger, protecting their safety takes priority over keeping their suicidal thoughts secret.

8. Help create immediate safety.
If there is imminent risk, stay with the person and seek emergency assistance.

DON’T:

1. Don’t argue with their feelings.

Avoid responses such as, “You have so much to live for,” as a way of shutting down the conversation.

2. Don’t shame them.

Avoid telling them that they are weak, selfish, ungrateful, or disappointing God.

3. Don’t lecture them.

A person in crisis needs connection and safety before a long lecture.

4. Don’t dismiss their pain.

Statements such as “Other people have it worse” can make someone feel even more alone.

5. Don’t promise secrecy.

If someone’s life is at risk, you may need to tell a trusted person or professional who can help keep them safe.

6. Don’t leave someone alone when there is immediate danger.

Seek urgent professional or emergency assistance instead.

Suicide Prevention

Prevention also means building protective factors before a crisis occurs.

Protective factors can include:

  • Access to appropriate mental health care
  • Early treatment of mental health difficulties
  • Strong relationships with family and friends
  • Connection to supportive communities
  • Healthy problem-solving and coping skills
  • A sense of purpose and belonging
  • Safe and supportive faith communities
  • Cultural or religious beliefs that encourage help-seeking and connection
  • Reducing access to lethal means when someone is at risk
  • Developing healthy ways to manage stress and emotional pain

A person does not have to wait until they are suicidal before seeking help.

Choosing Hope in the Middle of Pain

For Christians, suicide prevention is not simply about telling someone to “pray harder” or quoting Scripture at them.

Faith and professional mental health care do not have to compete with one another. Joyce Meyer has often spoken about the importance of seeking help and not being ashamed to admit when you’re struggling.

Seeking help does not make you a weak Christian.

You can have faith in God and still need support. You can pray and still talk to a counselor. You can trust God and still ask someone to walk with you through a difficult season.

Asking for help is not a failure of faith. Sometimes, God answers our prayers through the people He places around us.

Prayer, Scripture, pastoral support, Christian community, counseling, medical care, and other appropriate forms of support can work together.

The Bible also gives us examples of people who experienced profound emotional distress.

Elijah Wanted to Die

In 1 Kings 19:1–18, Elijah became exhausted, afraid, and deeply discouraged. He reached a point where he asked God to take his life.

Notice God’s response.

God did not shame Elijah for being overwhelmed.

Elijah was given rest, food, God’s presence, and renewed direction.

Moses Became Overwhelmed

In Numbers 11:10–17, Moses became so overwhelmed by the burden he was carrying that he expressed a desire for his life to end.

God responded by providing help and people to share the responsibility.

This reminds us that we were never designed to carry every burden alone.

Job Experienced Deep Despair

Job expressed profound despair throughout the book of Job, including in Job 3, Job 6:8–13, and Job 30:20–23.

Yet Job’s suffering was not the end of his story.

His experience reminds us that a person’s darkest chapter does not necessarily determine how their story ends.

Bible Verses to Hold Onto When Life Feels Too Painful

When you feel broken or overwhelmed

  • Psalm 34:17–18 — God is near to the brokenhearted and those crushed in spirit.
  • Psalm 42:5 — Speaking hope to your own soul when you feel downcast.
  • Psalm 55:22 — Giving your burdens to God and trusting Him to sustain you.
  • Psalm 61:1–2 — Crying out to God when your heart is overwhelmed.
  • Psalm 73:26 — God remains your strength even when your heart and body fail.
  • Psalm 147:3 — God heals the brokenhearted.
  • Isaiah 41:10 — God promises His presence, strength, help, and support.
  • Isaiah 43:1–2 — God promises to be with His people through overwhelming circumstances.

When you feel like there is no hope

  • Lamentations 3:21–24 — Remembering God’s faithfulness when circumstances feel hopeless.
  • Romans 5:3–5 — Suffering can produce perseverance, character, and hope.
  • Romans 8:18 — Present suffering is not the end of the story.
  • Romans 8:28 — God can work through circumstances for the good of those who love Him.
  • Romans 8:31–32 — God is for His people.
  • Romans 8:35–39 — Nothing can separate believers from the love of God in Christ.
  • 2 Corinthians 4:8–9 — Being pressured and struck down does not mean being destroyed.
  • 2 Corinthians 4:16–18 — Present suffering is not the entirety of our reality.

Your life has value

  • Genesis 1:26–27 — Humanity is created in God’s image.
  • Psalm 139:13–18 — God knows and formed us intimately.
  • 1 Corinthians 6:19–20 — Our bodies belong to God.
  • Acts 17:25–28 — God gives life and breath.
  • Ephesians 2:10 — We are God’s workmanship, created for good works.

When you are going through a crisis

  • 1 Corinthians 10:13 — God provides a way through temptation and testing.
  • James 1:2–4 — Trials can produce endurance.
  • Hebrews 4:15–16 — We can approach God for mercy and help.
  • Philippians 4:6–7 — Bring anxiety and distress to God and seek His peace.
  • 1 Peter 5:7 — Give your worries to God because He cares for you.

If You Are Thinking About Suicide Right Now

Please do not face the moment alone.

Move away from anything you could use to hurt yourself and get around another person. Tell someone you trust exactly what is happening.

You can say:

“I am thinking about suicide, and I don’t feel safe being alone right now. Please stay with me and help me get support.”

If you believe you may act on suicidal thoughts or have already harmed yourself, seek emergency medical help immediately.

You do not need to solve your entire life today. The feelings you are experiencing may be intense, but feelings can change. Circumstances can change. Treatment can help. People can help. God can meet you in places of profound pain.


Depression in Older Adults: Aging and Emotional Health

It’s normal to feel sad sometimes. But if your sadness lasts two weeks or longer and affects your ability to handle daily life, it could be depression.

According to the National Institute on Aging (NIA), depression is not a normal part of getting older—and the good news is, it’s treatable at any age.

Erik Erikson’s Integrity vs. Despair

Psychologist Erik Erikson described eight stages of life. The final stage, Integrity vs. Despair, occurs from around age 65 until death. During this stage, older adults look back on their lives and reflect on what they’ve done, who they’ve loved, and what they’ve achieved.

Integrity

Integrity is a sense of peace and satisfaction with one’s life journey.

  • Characteristics: Gratitude, acceptance of mistakes, and appreciation for meaningful accomplishments.

  • Outcome: A sense of wholeness and the ability to face death calmly, with wisdom.

Despair

Feelings of bitterness and regret over missed opportunities.

  • Characteristics: Fear of death, hopelessness, and dissatisfaction with how life turned out.

  • Outcome: Emotional distress, which can deepen into depression if not addressed.

Reaching integrity can bring wisdom and peace, while despair can lead to sadness, regret, and isolation, making older adults more vulnerable to mental health challenges like depression.

Depression in Old Age

More than 1 in 10 older adults experience depression. Among those in residential care homes, the rate rises to over 3 in 10.

Yet, many cases go unnoticed because symptoms are often mistaken for “just getting old.”

Common Risk Factors

  • Chronic medical conditions (like heart disease or arthritis)

  • Family or personal history of depression

  • Stressful life events

  • Poor sleep or sleep disorders

  • Lack of exercise or physical activity

  • Social isolation or loneliness

  • Loss of a loved one

Warning Signs of Depression in Seniors

Depression may not always appear as sadness. Look out for:

  • Difficulty sleeping or sleeping too much

  • Fatigue or loss of energy

  • Weight loss or changes in appetite

  • Withdrawal from friends or activities

  • Neglecting personal care

  • Increased alcohol use

  • Talking about death or giving away possessions

If an older person is talking about death, changing their will, or isolating themselves, take it seriously. These may be signs of suicidal thoughts.

Need immediate help?
Call the 988 Suicide & Crisis Lifeline at 988 (available 24/7) or visit 988lifeline.org.
For TTY users, dial 711 then 988 or 800-799-4889.

How to Support an Older Adult Living with Depression

Depression can make people withdraw, but connection helps healing.
Here’s how you can support an older friend, neighbor, or family member:

  • Invite them for a walk, coffee, or shared activity

  • Encourage them to talk to their doctor, depression can be treated at any age

  • Listen without judgment

  • Help them stay connected through visits, calls, or social events

Loneliness is one of the biggest causes of depression in older adults. A simple chat or visit can make a world of difference.

Treatment Options for Depression in Older Adults

Treatments work, but patience is key. Antidepressants may take longer to show results in older adults, and therapy needs to be tailored for their unique needs.

Common Treatments

  • Antidepressant medications (6–8 weeks for full effect)

  • Cognitive Behavioral Therapy (CBT) to reframe negative thoughts

  • Exercise and social engagement to boost mood

  • Electroconvulsive Therapy (ECT) for severe or treatment-resistant cases

  • Music or art therapy to promote emotional release and joy

A combination of medical, social, and psychological support often provides the best outcome.

Protecting Mental and Emotional Health as You Age

It’s never too late to build habits that support emotional well-being.

Simple Ways to Prevent Depression

  • Stay physically active (even short walks help)

  • Get 7–9 hours of sleep per night

  • Keep in touch with family and friends

  • Eat nutritious meals

  • Engage in hobbies and community activities

  • Seek medical advice for any persistent low mood or sleep issues

Sleep and Mental Health in Older Adults

Sleep changes with age. Many older adults experience:

  • Lighter sleep and more awakenings

  • Earlier bedtimes and wake times

  • Difficulty falling or staying asleep

Why It Happens

  • A weakened circadian rhythm and reduced melatonin production

  • Chronic health issues like pain or breathing problems

  • Medications that disrupt sleep

  • Reduced activity and sunlight exposure

  • Depression and anxiety

How to Sleep Better

  • Go to bed and wake up at the same time daily

  • Keep your bedroom quiet, dark, and cool

  • Limit caffeine, alcohol, and nicotine

  • Exercise during the day, but not before bed

  • Avoid heavy meals and reduce liquids at night

  • If you can’t sleep after 30 minutes, get up and do something relaxing

  • Talk to your doctor about insomnia or medication side effects

Good sleep not only boosts mood but also helps memory, focus, and overall quality of life.

Conclusion

Aging comes with wisdom and experience, but also change and reflection.

When older adults struggle to find peace with their past or lose a sense of purpose, depression can quietly creep in.

By staying connected, seeking help early, and understanding the emotional journey of later life, older adults can rediscover hope, peace, and integrity and continue to live meaningfully.

If you found this helpful, share it to raise awareness about mental health in older adults.

12 Tips to Consider when Caring for Someone with Parkinson’s

couples holding hands

Caring for a loved one with Parkinson’s disease (PD) can be a deeply rewarding experience, but it also comes with challenges that test patience, resilience, and adaptability. Parkinson’s affects movement, mood, and cognition, and its symptoms can vary daily. For caregivers, understanding the disease and implementing practical strategies can make a huge difference for both the patient and themselves.

This guide covers everything you need to know to provide compassionate, safe, and effective care. But First lets take a look at Maria’s Journey

woman with Parkinson's disease walking down the road

What Maria Taught us about Caregiving

Maria was 32 when her father, Samuel, was diagnosed with Parkinson’s disease. At first, the tremors in his hands seemed minor—sometimes spilling a cup of coffee or dropping his keys. But over time, the stiffness in his legs and slowness in movement became more noticeable.

Maria worked full-time but decided to become her father’s primary caregiver. The first few months were overwhelming. She struggled to keep track of his medication schedule, worried constantly about him falling, and felt guilty when she needed a break. Samuel, proud and independent, sometimes resisted her help, which made communication tense.

Determined to make it work, Maria started educating herself about Parkinson’s. She learned about exercises that improved balance, adaptive tools to help her father dress and groom himself, and ways to manage constipation with a fiber-rich diet. She set up pill organizers and alarms to make sure medications were taken on time, and she rearranged the house to reduce tripping hazards.

Even with all her planning, the emotional toll was heavy. Maria realized she was experiencing caregiver stress—she felt exhausted and anxious. She turned to a local Parkinson’s support group and learned about respite care, giving herself a few hours each week to rest while a trained caregiver helped her father. She also built a “backup team” of cousins and neighbors who could step in when needed.

Months later, Maria noticed a change—not just in her father, who seemed more confident walking with his cane and less frustrated during meals, but in herself. She felt more prepared, less stressed, and more capable of providing compassionate care. She learned that caregiving isn’t just about doing tasks; it’s about patience, communication, and building a support system that works for both the caregiver and the loved one.

1. Be Honest with Each Other

Open communication is the foundation of caregiving. Discuss symptoms, daily struggles, and emotional experiences with your loved one. Parkinson’s can affect mood and cognition, which may lead to frustration or anxiety. Honest conversations help you understand their priorities, fears, and limitations, and allow them to participate in decisions about their care.

Tip: Schedule a weekly check-in to discuss how they’re feeling and what adjustments might be needed.

2. Educate Yourself

The more you know about Parkinson’s, the better you can anticipate challenges. Learn about:

  • Motor symptoms: tremors, rigidity, slow movements, and balance issues.

  • Non-motor symptoms: depression, anxiety, sleep disturbances, and cognitive changes.

  • Treatment options: medications, therapies, and lifestyle adjustments.

Tip: Join support groups or follow Parkinson’s organizations online for up-to-date resources and practical advice.

3. Attend Doctor’s Appointments

Accompany your loved one to appointments whenever possible. This ensures:

  • You fully understand the treatment plan.

  • You can monitor medication effectiveness and side effects.

  • You can report new symptoms your loved one may not notice.

Tip: Take notes during appointments or record questions in advance to make sure nothing is missed.

4. Stay on Top of Insurance

Parkinson’s care can involve medications, physical therapy, and specialized equipment. Keep track of:

  • Health insurance coverage

  • Prescription plans

  • Medical bills and reimbursements

Being proactive prevents last-minute stress and ensures uninterrupted care.

5. Be Flexible

Parkinson’s symptoms can fluctuate from day to day, or even hour to hour. Some days, tasks like walking or eating may be harder. Be ready to adjust routines, schedules, or expectations based on how your loved one feels.

Tip: Focus on what can be done rather than what can’t, celebrating small victories maintains morale.

6. Make Sure Medications Are Taken on Time

Medication timing is critical for managing Parkinson’s symptoms. Missed or delayed doses can lead to:

  • Increased tremors

  • Stiffness

  • Slowness in movement

Tip: Use pill organizers, alarms, or smartphone reminders. Keep a medication log to track doses and any side effects.

7. Use Tools to Make Grooming Easy

Parkinson’s can make fine motor tasks challenging. Adaptive tools can maintain independence and reduce frustration:

  • Electric toothbrushes and razors

  • Button hooks or zipper pulls for clothing

  • Long-handled grooming brushes

Tip: Encourage independence where possible, it boosts confidence and dignity.

8. Avoid Shoes with Rubber Soles

Shoes with rubber soles can create friction, making shuffling or walking unstable. Opt for:

  • Shoes with smooth, firm soles

  • Proper-fitting footwear to prevent trips and falls

  • Non-slip indoor slippers

Tip: Always keep walking paths clear and well-lit.

  1. Provide Fiber-Rich Foods to Prevent Constipation

Constipation is a common non-motor symptom of Parkinson’s. Include:

  • Fresh fruits and vegetables

  • Whole grains and legumes

  • Adequate water intake

Tip: Regular meals, hydration, and gentle exercise like walking or stretching can help digestive health.

10. Recognize Caregiver Stress, Strain, and Burnout

Caring for someone with Parkinson’s can be physically, emotionally, and mentally taxing. Common issues include:

  • Stress: Worry about your loved one’s health or daily tasks

  • Strain: Physical exhaustion from lifting, assisting, or household duties

  • Burnout: Feeling overwhelmed, irritable, or disconnected

Use tools like the Caregiver Stress Inventory to evaluate your wellbeing. Being proactive about your mental and physical health is just as important as caring for your loved one.

11. Build a Backup Team

You don’t have to manage everything alone. Build a network of:

  • Family members or friends

  • Professional caregivers or home aides

  • Community support groups

A reliable support system ensures consistent care, especially during emergencies or when you need a break.

  1. Consider Respite Care

Respite care provides temporary relief for caregivers. Options include:

  • In-home professional care for a few hours or days

  • Short-term stays in a care facility

  • Community programs or adult day care

Taking time for yourself helps prevent burnout, reduces stress, and allows you to recharge while ensuring your loved one is safe and cared for.

In conclusion

Caring for someone with Parkinson’s requires patience, flexibility, and preparation. By educating yourself, supporting medication adherence, ensuring safety, and taking care of your own wellbeing, you can provide compassionate, high-quality care.

Remember, you’re not alone. Building a support system, using adaptive tools, and seeking help when needed ensures both you and your loved one thrive despite the challenges of Parkinson’s disease.

Parkinson’s Symptoms: When to Worry and When It’s Normal

It’s normal to notice little changes in your body as you get older, your handwriting might shrink, your sleep may not feel as deep, or you might walk a little slower than you used to. But sometimes, these everyday changes overlap with early signs of Parkinson’s disease, a brain condition that affects movement and other functions.

So how do you know when it’s just aging or stress, and when it’s something worth bringing up with your doctor? Let’s break it down symptom by symptom.

Parkinson disease

Tremor

Tremors are a common concern. Many people experience mild shaking after stress, fatigue, or too much caffeine, and tremors that only appear when you’re using your hand are usually harmless. The tremors linked to Parkinson’s, however, are different, they tend to appear when the hand is resting, often starting on one side of the body, and they gradually become more noticeable over time.

  • When it’s normal: Stress, caffeine, or even fatigue can make your hands shake a little. Tremors that only show up when you’re using your hand (like holding a cup of coffee) are usually harmless.
  • When to worry: Tremors that happen when your hand is resting, start on one side of the body, or slowly get worse over time may be linked to Parkinson’s.

Small Handwriting

Handwriting can also reveal early warning signs. While arthritis, vision problems, or simply aging can make writing smaller, Parkinson’s may cause a condition called micrographia, where handwriting becomes progressively cramped and tiny.

  • When it’s normal: Aging, arthritis, or poor vision can make your writing smaller or a bit shaky.
  • When to worry: If your handwriting becomes progressively tiny and cramped (called micrographia), it could be an early sign of Parkinson’s.

Loss of Smell

  • When it’s normal: Allergies, sinus infections, or even a recent cold (including COVID-19) can block your sense of smell temporarily.
  • When to worry: A slow, unexplained loss of smell, especially when it doesn’t improve after the infection clears can be an early warning sign.

Trouble Sleeping

Trouble sleeping often seems harmless as well, since stress or a poor routine can keep you awake. The difference with Parkinson’s is when sleep problems include acting out dreams—such as kicking, punching, or talking in your sleep or having restless nights regularly.

  • When it’s normal: Stress, caffeine, or a poor bedtime routine can make it hard to sleep.
  • When to worry: If you’re acting out dreams (talking, kicking, punching in your sleep) or having restless nights regularly, it may be connected to Parkinson’s.

Trouble Walking

  • When it’s normal: Sore muscles, bad shoes, or fatigue can make walking awkward sometimes.
  • When to worry: Shuffling steps, dragging your feet, difficulty starting to walk, or reduced arm swing are more concerning.

Constipation

Constipation is common for many reasons, including diet and dehydration, but when it persists despite healthy habits, it may indicate a neurological cause. Similarly, dizziness and fainting can happen if you stand up too quickly or don’t drink enough water, but frequent unexplained episodes may be related to Parkinson’s effects on blood pressure.

  • When it’s normal: A low-fiber diet, dehydration, or travel can slow digestion.
  • When to worry: Ongoing constipation that doesn’t improve with lifestyle changes, especially if paired with other symptoms, may be a Parkinson’s sign.

Dizziness and Fainting

  • When it’s normal: Standing up too quickly, skipping meals, or not drinking enough water can make you lightheaded.
  • When to worry: Frequent dizziness or fainting without clear cause can be linked to blood pressure changes seen in Parkinson’s.

Soft or Low Voice

  • When it’s normal: A sore throat, fatigue, or talking too much can make your voice softer.
  • When to worry: If your voice becomes consistently softer, hoarse, or monotone, it may be related to Parkinson’s.

Stooping or Masked Face

  • When it’s normal: Sitting at a desk for long hours or weak back muscles can cause posture issues.
  • When to worry: A persistent stooped posture or a face that looks blank, with less blinking and fewer expressions, are red flags.

Mood and Motivation Changes

Mood and motivation can also shift. Stressful life events can cause low mood or lack of energy, but depression and apathy that last for months, especially without clear cause, may be part of Parkinson’s. Even erectile dysfunction, which can stem from age, stress, or other health conditions, may be related when it occurs alongside these other changes.

  • Depression & apathy
    • Normal: Stressful life events can affect your mood or energy.
    • Worry: Long-term low mood, loss of interest, or withdrawal from activities without a clear reason.
  • Erectile dysfunction
    • Normal: Common with age, stress, or medical conditions like diabetes.
    • Worry: Persistent problems alongside other Parkinson’s signs may be linked.

How Is Parkinson’s Diagnosed?

Parkinson’s is not diagnosed through a single test. Instead, doctors rely on a detailed medical history, a neurological exam that looks at movement, balance, reflexes, and handwriting, and sometimes a trial of Parkinson’s medication, if symptoms improve, that supports the diagnosis. Imaging like a DaTscan or MRI may be used to rule out other conditions but isn’t always necessary. A neurologist, especially one specializing in movement disorders, usually makes the diagnosis.

Conclusion

Having one symptom on this list does not mean you have Parkinson’s. Many of these changes can be caused by stress, aging, or other medical issues.

What matters is persistence and combination, if several symptoms appear together, or if one keeps getting worse, it’s worth seeing a doctor.

Early diagnosis can help you manage symptoms, stay active, and protect your quality of life. If you’re concerned, don’t wait, schedule an appointment with your healthcare provider.

Night Shifts Are Secretly Making You Gain Weight

In today’s 24/7 world, millions of people work nights, rotating shifts, or irregular schedules to keep essential services running. From nurses and factory workers to security officers and hospitality staff, shift work is a necessity for modern life. But while this lifestyle supports the economy, it can take a serious toll on your health, particularly your weight.

Research shows that shift workers are significantly more likely to gain weight and develop obesity than those who work traditional daytime hours. Even more concerning, shift work increases the risk of type 2 diabetes and other chronic diseases. But why does this happen, and what can you do to protect yourself? Let’s explore the science and practical solutions.

My Experience as a Shift Worker

I’ve worked different shifts, and honestly, morning shifts are my favorite. But there are times when we don’t have a choice and must take on the night shift, too.

During my night shifts, I’ve noticed a pattern:

  • During the day, I’m too tired to go out and too sleepy to even think about going to the gym.
  • I have a gym membership — but I haven’t gone in weeks.
  • I find myself craving sugary snacks and high-fat foods like fried chicken and pizza.

It’s not that I don’t want to make better choices — it’s just harder when you’re exhausted. That’s exactly why I decided to write this blog. I’ve learned that if we replace high-fat snacks and sugary drinks with water, tea, and healthy foods, and find moments to move our bodies when we can, it makes a big difference.

I also believe in prioritizing breaks for mental health-boosting activities or even a short walk. Personally, during my breaks, I like to pray and ask God to help me be a good representative of Him.

weight gain

Why Shift Work Can Lead to Weight Gain

The main culprit is circadian rhythm disruption,  your body’s natural 24-hour clock that regulates hormones, digestion, and metabolism. When you work at night or rotate between day and night shifts, your body gets mixed signals about when to eat, sleep, and burn energy.

This disruption can cause hormonal changes that increase ghrelin (the hunger hormone) and decrease leptin (the satiety hormone), making you feel hungrier and less satisfied after eating. Over time, these changes promote overeating, fat storage, and weight gain.

Shift work can also elevate cortisol, the stress hormone, which encourages fat accumulation, especially around your abdomen.

Lifestyle Patterns That Worsen the Risk

In addition to circadian disruption, shift workers often develop habits that make weight management harder:

  1. Lower Physical Activity
    Working at odd hours often leaves you feeling too tired to exercise. Gyms may be closed when you’re free, and you may lack the energy for structured workouts.

  2. Poor Diet Quality
    Studies show shift workers tend to eat fewer fruits and vegetables and rely more on processed snacks, sugary drinks, and fast food — especially during night shifts when healthy options are limited.

  3. Poor Sleep Quality
    Perhaps the biggest factor linking shift work and weight gain is poor sleep. Sleeping during the day is harder, and even when you do sleep, it’s often shorter and less restorative. Sleep deprivation disrupts hunger-regulating hormones and slows metabolism.

  4. Higher Smoking Rates
    Some shift workers turn to smoking to stay alert. While nicotine can suppress appetite, smoking damages your health in countless ways and is not a safe or sustainable solution.

How Poor Sleep Drives Weight Gain and Diabetes

Among all the lifestyle factors, poor sleep stands out as the strongest link between shift work, obesity, and type 2 diabetes. Inadequate sleep:

  • Increases cravings for high-calorie, sugary foods.

  • Reduces your ability to control portion sizes.

  • Slows your metabolism, making it easier to gain weight.

  • Impairs insulin sensitivity, increasing the risk of type 2 diabetes.

One large study found that shift workers with poor sleep quality had a significantly higher risk of obesity and diabetes even after accounting for diet and exercise. That means improving sleep quality is one of the most important ways to prevent weight gain.

How to Prevent Weight Gain When You Work Shifts

If you are intentional, you can protect your health with targeted strategies. Here’s how:

1. Prioritize High-Quality Sleep

  • Keep a consistent sleep schedule — even on your days off.

  • Create a dark, quiet sleep environment with blackout curtains, an eye mask, and white noise.

  • Avoid caffeine and heavy meals within six hours of bedtime.

  • Consider short naps before night shifts to reduce fatigue.

2. Stay Active — Even in Short Bursts

  • Aim for at least 150 minutes of moderate activity per week.

  • Break it into 10–20 minute sessions if your schedule is unpredictable.

  • Take brisk walks during breaks or stretch between tasks.

  • Try bodyweight exercises at home when you can’t get to the gym.

3. Eat Smart and Plan Ahead

  • Pack healthy meals and snacks before your shift so you’re not relying on vending machines or takeout. You can pack snacks like cucumber slices, berries and orange slices.

  • Include lean proteins, whole grains, fruits, vegetables, and healthy fats in your diet.

  • Eat at regular times whenever possible to keep your metabolism steady.

  • Limit high-sugar and high-fat snacks, especially late at night.

4. Reduce Smoking and Alcohol

  • Smoking may seem like a way to curb appetite or stay awake, but it increases your risk for heart disease, cancer, and poor sleep.

  • Alcohol can make you drowsy initially but disrupts deep sleep, leaving you more fatigued.

  • Seek healthier stress relief options like meditation, praying, reading, or light exercise.

5. Manage Stress Proactively

  • Practice mindfulness or deep breathing during breaks.

  • Connect with supportive coworkers or friends who understand your schedule.

  • Use relaxation techniques before bed to help your body unwind.

Conclusion

Working shifts doesn’t have to mean sacrificing your health. By prioritizing sleep, eating balanced meals, staying active, and managing stress, you can significantly lower your risk of weight gain and long-term health problems.

Small, consistent changes add up. Even if you can’t control your work schedule, you can control how you care for your body. Protecting your health today means you’ll have more energy, better mood, and a lower risk of chronic illness in the years to come.

Did you find this blog post helpful? Leave a comment below.

7 Proven Tips to Beat Shift Work Fatigue Naturally

woman working shift work

If you’ve ever struggled to stay awake during a night shift or felt exhausted during your days off, you’re not alone. Shift work fatigue is a common challenge faced by millions of workers across various industries from healthcare and security to customer service and manufacturing. The irregular hours and disrupted sleep patterns can take a toll on your body and mind. But the good news is, there are natural ways to fight back.

Here are seven proven tips to help you beat shift work fatigue naturally, so you can stay alert, energized, and healthy.

1. Sleep Smart

When it comes to reducing shift work fatigue, improving your sleep quality is just as important as the amount of sleep you get. Because shift workers often sleep during the day, their rest is lighter and more prone to interruptions. To improve sleep naturally, start by going to bed and waking up at the same time every day—even on your days off. A consistent sleep schedule helps your body regulate its internal clock. Using blackout curtains or sleep masks can help block daylight, and white noise machines can drown out external sounds that might otherwise disturb your rest. You should also avoid alcohol before bed.

While it may make you feel drowsy, alcohol interferes with REM sleep—the deep, restorative stage you need to wake up refreshed. If you’re struggling to unwind before bedtime, take 30 minutes to relax away from screens and stressful activities.

2. Power Nap When You Can

If you’re exhausted during your shift and don’t feel up to exercising during your break, a short nap can do wonders. A nap of 10 to 20 minutes is considered ideal. It’s short enough to help you recharge without entering deep sleep, which can leave you feeling groggy when it’s time to get back to work.

For some shift workers, a technique known as the “coffee nap” is especially effective. This involves drinking a cup of coffee just before lying down for a 15–20 minute nap. Since caffeine takes about 20 minutes to kick in, you’ll wake up right as the coffee begins to work its magic, feeling doubly refreshed and alert. This simple hack combines the benefits of both rest and a mild stimulant, making it a smart strategy for tired shift workers.

3. Use Caffeine Carefully and Strategically

Caffeine can be a helpful tool, but only when used in moderation and at the right times. A cup of coffee or caffeinated soda at the beginning of your shift can provide a much-needed energy boost. Since caffeine typically takes 15 to 20 minutes to take effect, it’s wise to consume it early on rather than waiting until you’re already feeling drowsy.

Instead of relying on one big dose, moderate amounts of caffeine every one to two hours tend to work better for sustained energy. That said, it’s crucial to avoid caffeine in the three to four hours before you plan to sleep. Drinking coffee or energy drinks too late can interfere with your ability to fall asleep and reduce the quality of your rest. Managing caffeine wisely helps ensure you stay alert when needed without sabotaging your sleep.

4. Eat Often to Maintain Energy

Food is fuel, and the way you eat during your shift can directly impact how tired or energized you feel. Eating large meals can weigh you down, making you feel sluggish, especially if you’re sitting for most of your shift. A better approach is to eat regular meals and healthy snacks every three to four hours. This keeps your blood sugar stable and gives your body a consistent supply of energy.

Focus on whole, balanced meals that include lean proteins, healthy fats, complex carbohydrates, and fiber. Try to avoid sugary snacks and greasy foods, as they tend to cause energy crashes later.

5. Exercise

Exercise may be the last thing on your mind when you’re tired, but it’s one of the best ways to fight fatigue in the long run. Even a short 15-minute walk can increase circulation, elevate your mood, and give you a quick energy boost. If you’re just starting out, don’t pressure yourself into doing intense workouts.

Begin with small amounts of movement and gradually build up your activity level. Over time, aim for at least two and a half hours of moderate-intensity aerobic exercise per week, such as brisk walking or cycling. Regular exercise helps your body adapt to unusual sleep schedules and improves the quality of your rest. In the long run, moving more will actually help you feel less tired.

6. Stick to a Set Shift Pattern When Possible

Rotating shifts are one of the most challenging aspects of shift work. Constantly changing your schedule confuses your body’s internal clock, making it harder to fall asleep and wake up refreshed. If your job allows, try to stick to a consistent shift pattern. Working the same number of hours at the same time every day allows your body to adjust more effectively. Where possible, it’s also helpful to cluster similar shifts together—for example, doing several night shifts in a row.

If you’re about to return to night work after some time off, try staying up as late as possible the night before to ease the transition. While not all workers can choose their shift schedule, keeping it as consistent as possible can significantly reduce fatigue and improve your overall health.

7. Hydrate Often and Avoid Alcohol

Hydration plays a major role in energy levels and mental clarity. When you’re dehydrated, you may experience headaches, fatigue, dizziness, and trouble concentrating. That’s why it’s important to drink water regularly throughout your shift.

Aim for 12 to 16 cups of water a day, depending on your activity level and environment. Water helps transport nutrients, regulate body temperature, and keep your organs functioning properly. At the same time, try to limit sugary sodas and high-caffeine energy drinks, which can lead to dehydration and blood sugar crashes.

Having a durable, insulated water bottle by your side can make it easier to sip consistently throughout your shift and avoid energy dips caused by dehydration.

Conclusion

Shift work fatigue is a real challenge, but it doesn’t have to control your life. With the right strategies—like improving your sleep, eating smart, staying hydrated, managing caffeine, and moving regularly—you can fight fatigue naturally and feel more like yourself again. Start by applying just one or two of these tips, and build up over time. The more consistent your healthy habits become, the better equipped your body will be to handle the demands of shift work.

If you’re a shift worker struggling with constant tiredness, know that small changes add up. You deserve to feel well regardless of your schedule.

The Best Sleep Schedule for Shift Workers

shift worker scratching his eye

Shift work is essential in many industries e.g healthcare, transportation and  security but it comes with a major health cost: chronic sleep deprivation.

Whether you work nights, rotating shifts, or early mornings, your sleep is often out of sync with your body’s natural circadian rhythm. Over time, this can lead to poor concentration, memory lapses, mood disturbances, and even serious health conditions.

In this post, we’ll dive into the best sleep schedule strategies for shift workers, based on research from UCLA Health, the Sleep Foundation, and other expert sources. We’ll cover how to create a sleep routine that supports both your body and your work schedule and how to make sleep a priority, even in a noisy, unpredictable world.

Why Sleep Is Non-Negotiable for Shift Workers

black woman sleeping

According to UCLA Health, sleepiness can have a negative impact on nearly every part of your functioning, including:

  • Attention
  • Concentration
  • Reaction time
  • Memory
  • Mood

Shift workers are especially at risk because most struggle to get enough quality rest. Working at night and sleeping during the day disrupts your internal clock, making it harder to fall and stay asleep. Over time, this can impair job performance and raise your risk for chronic issues such as obesity, diabetes, cardiovascular disease, and mental health disorders.

Start With Your Personal Sleep Profile

Before designing a sleep schedule, it’s important to evaluate:

  • Your individual needs – Some people need 7 hours of sleep, others function best with 9.
  • The demands of your job – Are your shifts rotating or consistent? Do you work early mornings or overnights?
  • Your home environment – Do you live with others? Are there children, pets, or noise that might disrupt your sleep?

Understanding these factors will help you develop a plan that’s realistic and effective.

The Ideal Sleep Schedule for Night Shift Workers

One of the best ways to reduce sleep disruption is to stick to the same sleep schedule every day, even on your days off. For example, if you usually sleep from 9 a.m. to 5 p.m. after your shift, continue sleeping during that window on weekends too.

Shifting back to nighttime sleep during your off days can confuse your body clock and make it harder to sleep during the day once your work week resumes.

Aim to get 7–9 hours of sleep within each 24-hour period. If this isn’t possible in one stretch, consider splitting your sleep into two periods (e.g., a 6-hour core sleep and a 90-minute nap later).

Strategic Napping

Well-timed naps can be highly effective for staying alert and avoiding drowsiness-related accidents.

  • Pre-shift nap: Take a 90-minute nap in the late afternoon or evening before your night shift. This helps reduce sleep pressure and increases alertness during your shift.
  • Mid-shift nap (if possible): A short 15–30-minute nap during a break can help combat fatigue.
  • Post-shift nap: If you feel drowsy before driving home, take a 15-minute nap in your car. Studies show that the hours between midnight and 6 a.m. are the most dangerous for drowsy driving.

Managing Light Exposure to Support Sleep

Your body clock is heavily influenced by light. Use this to your advantage:

  • During your shift: Use bright indoor lighting to help stay alert.
  • After your shift: Avoid natural sunlight by wearing dark sunglasses on your way home.
  • Before bed: Keep your bedroom dark by using blackout curtains or a sleep mask.
  • Noise control: Use a white noise machine, fan, or earplugs to drown out daytime sounds.

Ask family members or housemates to avoid making noise during your sleep hours. Schedule household chores, repairs, and deliveries for times when you’re awake.

Smart Caffeine and Stimulant Use

Caffeine can help improve alertness on the job, but timing is key.

  • Use caffeine at the beginning of your shift to stay focused.
  • Avoid caffeine within 4 hours of your intended bedtime, as it can delay sleep and reduce quality.
  • Be cautious with energy drinks and stimulants; they can lead to crashes and worsen sleep issues over time.

Fuel Your Body with the Right Foods

Shift workers are more likely to experience gastrointestinal issues, in part because of irregular eating patterns.

To improve digestion and support better sleep:

  • Eat three balanced meals spaced throughout the day (or night).
  • Avoid heavy, greasy, or spicy meals before bed.
  • Stay hydrated, but limit fluids 1–2 hours before bedtime to avoid nighttime bathroom trips.
  • Include fiber-rich foods and lean protein to help you feel full longer.

Rethink Alcohol, Nicotine, and Medication

  • Alcohol may make you feel sleepy, but it disrupts REM sleep and reduces sleep quality.
  • Nicotine is a stimulant and can make it harder to fall asleep or stay asleep.
  • Prescription medications and over-the-counter supplements may affect your sleep. Speak with your doctor if you suspect your medication interferes with rest.

Build a Bedtime Routine that Works for You

Just like infants, adults benefit from bedtime rituals. These can help signal to your brain that it’s time to wind down, even if it’s bright outside.

  • Take a warm shower, do light stretching, or practice deep breathing.
  • Avoid screens for 30–60 minutes before bed, as blue light disrupts melatonin production.
  • Keep your room cool, dark, and quiet.
  • Use your bed only for sleep and intimacy—don’t scroll, snack, or work in bed.

Transitioning to Days Off Without Losing Sleep

While it’s tempting to “flip” your sleep schedule on days off to enjoy daytime activities, doing so can backfire. Instead:

  • Keep your sleep and wake times consistent.
  • Use short naps to help adjust when needed.
  • If you must shift your schedule, do it gradually—by 1–2 hours at a time over a few days.

Conclusion

Sleep should never be an afterthought, even if your schedule is unpredictable. The health risks of chronic sleep deprivation are real, but with the right habits, shift workers can achieve consistent, restorative sleep.

Remember to prioritize a consistent routine, manage light and noise, and give your body the fuel and rest it needs to stay healthy and alert. Whether you’re starting a new night shift or trying to fix months of poor sleep, making these adjustments can transform how you feel on and off the clock.

Why Medical Students Face Higher Rates of Stress

“Physician, heal thyself” – but what happens when the healer is drowning in silence?

Sarah sat in the back row of her pharmacology lecture, mechanically taking notes while her mind spiraled into familiar territory. The material felt insurmountable, her latest exam score was disappointing, and she couldn’t shake the feeling that everyone around her was somehow more capable, more deserving of their white coat. What she didn’t realize was that nearly one in three of her classmates was experiencing similar thoughts – trapped in a cycle of perfectionism, comparison, and overwhelming pressure that has created a mental health crisis hiding in plain sight within medical education.

The statistics are both shocking and undeniable. While approximately 8% of the general population experiences depression, studies consistently show that 27% of medical students struggle with depressive symptoms – more than triple the rate of their peers. But the mental health crisis extends far beyond depression alone.

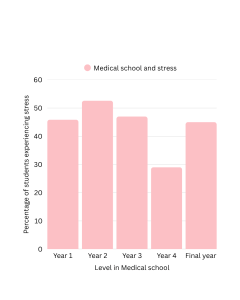
When we examine anxiety disorders, the picture becomes even more alarming. Research reveals that anxiety rates among medical students fluctuate dramatically throughout their education, creating a rollercoaster of psychological distress that tracks with the academic calendar. One comprehensive study found that anxiety affects 45.86% of first-year students, peaks at 52.58% in second year, remains elevated at 47.14% in third year, drops to 28.75% in fourth year, then rises again to 45.10% in the final year.

bar graph
Bar graph showing the percentage of students experiencing stress in different levels of medical school

These fluctuations tell a story of how different phases of medical education create unique psychological pressures. The initial shock of medical school intensity hits first-years hard, while second-year students face the notorious “pre-clinical to clinical” transition anxiety. Third-year students grapple with their first real patient responsibilities, fourth-years experience some relief as they near graduation, and final-year students face the stress of residency matching and career uncertainty.

The very individuals we’re training to heal others are experiencing mental health challenges at rates that would constitute a public health emergency in any other population.

The International Journal of Medical Education published a comprehensive meta-analysis in 2019 that examined 77 studies across different countries and cultures. The findings were consistent across geographic boundaries: medical students worldwide experience depression at rates 2.5 to 3 times higher than age-matched peers in other fields.

Why are so many medical students depressed?

The answer lies in a convergence of factors that create the perfect storm for mental health struggles. Medical students face a unique combination of extreme academic pressure, high-stakes testing, financial stress from significant debt, social isolation due to demanding schedules, and the psychological burden of preparing to hold lives in their hands.

Why do medical students have anxiety?

The anxiety epidemic stems from the uncertainty inherent in medical training. Students constantly face the unknown – will they pass their next exam? Will they match into their desired residency? Can they handle the responsibility of patient care? This chronic uncertainty, combined with perfectionist tendencies, creates persistent anxiety that can become debilitating.

Why are students more prone to depression?

Medical students are particularly vulnerable because they enter medical school as high achievers who have rarely experienced failure. When they encounter the normal struggles of medical education, they lack coping mechanisms for anything less than perfection. Additionally, the isolation from friends and family, financial pressures, and constant evaluation create a breeding ground for depressive symptoms.

What is the most stressful year of medical school? Based on anxiety data, second year emerges as the most psychologically challenging, with anxiety rates reaching 52.58%. This year combines intense studying for the first major licensing exam (USMLE Step 1) with the pressure of transitioning from basic sciences to clinical application – a combination that overwhelms more than half of all students.

Medical school attracts individuals who have spent their entire academic careers at the top of their class. These are students who have never encountered failure, who have built their identity around being the best, the brightest, the most capable. Then they enter medical school, where suddenly everyone is exceptionally talented.

Dr. Lisa Rotenstein, who has extensively researched medical student mental health, explains that this shift from being a big fish in a small pond to being surrounded by equally accomplished peers creates what psychologists call “the big fish-little pond effect.” For many students, this is their first encounter with academic struggle, and they lack the coping mechanisms to handle anything less than excellence.

The perfectionism that once served as a driving force becomes a destructive inner critic. Students begin to catastrophize normal academic challenges, viewing a single poor grade as evidence of their unworthiness to become a physician. This all-or-nothing thinking pattern, combined with the high stakes of medical education, creates a breeding ground for anxiety and depression.

The Imposter Syndrome Epidemic

“I don’t belong here.” “They made a mistake accepting me.” “Everyone else seems to understand this better than I do.” These thoughts plague medical students at alarming rates, creating what psychologists term “imposter syndrome” – the persistent feeling of being a fraud despite evidence of competence.

Medical education, with its emphasis on extensive knowledge and life-or-death decision-making, naturally amplifies these feelings. Students compare their internal struggles with their peers’ external composure, not realizing that everyone is fighting similar battles. The competitive atmosphere often discourages vulnerability and honest communication about difficulties, perpetuating the illusion that everyone else is managing better.

Maya, a third-year medical student, shared her experience: “I spent my first two years convinced that admissions had made an error. Every time I didn’t know an answer during rounds, I was sure my attending would realize I didn’t deserve to be there. It wasn’t until I started opening up to classmates that I realized we were all feeling the same way.”

Academic Pressure and the Stakes of Failure

Unlike other graduate programs, medical school carries the weight of future patient care. Students aren’t just worried about their GPA – they’re concerned that their academic performance directly correlates with their ability to save lives. This creates a unique psychological pressure that goes beyond normal academic stress.

The USMLE Step exams, residency applications, and clinical rotations all carry high stakes that can determine career trajectories. Students often report feeling that a single poor performance could derail their entire future, leading to chronic stress and anxiety that compounds over time.

Breaking the Stigma

Perhaps the most insidious aspect of this mental health crisis is the culture of silence that surrounds it. Medical students often fear that seeking help will be seen as weakness, that it will be documented in their records, or that it will prevent them from matching into competitive residencies.

This fear isn’t entirely unfounded. While progress has been made, some residency programs still ask about mental health history, and students worry about the implications of being honest about their struggles. The result is a culture where suffering in silence is normalized, where students push through depression and anxiety without seeking the help they desperately need.

Dr. Pamela Wible, a physician advocate for medical professionals’ mental health, describes this as “medical training trauma” – the normalization of abuse, neglect, and suffering as necessary components of becoming a physician. This toxic culture suggests that struggling with mental health indicates weakness or unsuitability for medicine, when in reality, it’s a natural human response to an unnaturally stressful environment.

Recognizing the Warning Signs

The tragedy of medical student mental health crises is that they’re often preventable with early recognition and intervention. Understanding the warning signs – both for oneself and for classmates – can be life-saving.

Physical symptoms often appear first: changes in sleep patterns, appetite fluctuations, frequent headaches, or unexplained fatigue. These may be dismissed as normal stress responses, but they often signal the beginning of more serious mental health challenges.

Cognitive changes include difficulty concentrating, memory problems, indecisiveness, or persistent negative thoughts. Students might notice that material that once came easily now feels impossible to grasp, or that they’re spending significantly more time studying with less retention.

Emotional indicators encompass feelings of hopelessness, excessive guilt, irritability, or emotional numbness. Some students report feeling like they’re “going through the motions” without experiencing genuine emotions.

Behavioral changes might include social withdrawal, neglecting self-care, increased substance use, or avoiding previously enjoyable activities. Students might stop exercising, eating poorly, or isolating themselves from friends and family.

Recognizing Signs in Classmates

Medical students often notice changes in their peers before recognizing them in themselves. Warning signs in classmates include dramatic changes in academic performance, increased absence from class or clinical rotations, social withdrawal, or comments about feeling hopeless or worthless.

The phrase “I’m just tired” becomes a common refrain that often masks deeper struggles. Students might joke about wanting to “disappear” or make offhand comments about not being cut out for medicine. These seemingly casual remarks often reflect genuine distress.

How Mental Health Impacts Medical Education

The consequences of untreated mental health issues extend far beyond individual suffering. Depression and anxiety significantly impact academic performance, with studies showing that medical students with untreated mental health conditions are more likely to struggle academically, drop out, or experience difficulties during clinical rotations.

More concerning is the impact on patient care. Students struggling with mental health issues report feeling less empathetic toward patients, making more medical errors, and experiencing greater difficulty with clinical decision-making. This creates a dangerous cycle where poor mental health leads to compromised patient care, which in turn increases guilt and worsens mental health symptoms.

The financial implications are also substantial. Medical education represents a significant investment, and mental health struggles can lead to academic delays, repeated coursework, or even withdrawal from medical school. The average medical student graduates with debt, making the consequences of mental health-related academic difficulties particularly devastating.

A Call for Change

Addressing the mental health crisis in medical education requires more than individual intervention. Medical schools are beginning to recognize this, implementing wellness curricula, providing mental health resources, and working to reduce stigma.

However, true change requires a fundamental shift in medical education culture. We must move away from the idea that suffering is necessary for becoming a good physician and toward a model that prioritizes well-being as essential for providing excellent patient care.

Students themselves play a crucial role in this cultural shift. By speaking openly about mental health struggles, supporting classmates, and prioritizing self-care, medical students can help create a more supportive environment for everyone.

The key is recognizing that seeking help for mental health struggles isn’t a sign of weakness – it’s a sign of strength and wisdom. Just as we wouldn’t expect someone to perform surgery with a broken hand, we shouldn’t expect students to navigate the challenges of medical education with untreated mental health conditions.

Resources and Next Steps

If you’re a medical student struggling with mental health issues, know that you’re not alone and that help is available. Most medical schools offer confidential counseling services, and many have specific programs designed for medical students.

Remember that seeking help early is always better than waiting until the situation becomes critical. Mental health treatment is not a luxury, it’s an essential component of your medical education and future practice.

Conclusion

The mental health crisis among medical students represents one of the most pressing challenges in medical education today. With depression rates three times higher than the general population, we can no longer afford to ignore this issue or dismiss it as a normal part of medical training.

By understanding the root causes – perfectionism, imposter syndrome, and overwhelming academic pressure – and recognizing the warning signs early, we can begin to address this crisis. More importantly, we can work to create a culture in medical education that values mental health as much as academic achievement.

If you’re struggling with mental health issues, please reach out for help. You deserve support, and seeking help makes you a better future physician, not a weaker one.

Sources:

  1. Rotenstein, L. S., et al. (2016). Prevalence of depression, depressive symptoms, and suicidal ideation among medical students. JAMA, 316(21), 2214-2236.
  2. Pacheco, J. P., et al. (2019). Mental health problems among medical students in Brazil. International Journal of Medical Education, 10, 224-230.
  3. Dyrbye, L. N., et al. (2014). Burnout and suicidal ideation among U.S. medical students. Annals of Internal Medicine, 149(5), 334-341.
  4. Mirza AA, Baig M, Beyari GM, Halawani MA, Mirza AA. Depression and Anxiety Among Medical Students: A Brief Overview. Adv Med Educ Pract. 2021 Apr 21;12:393-398. doi: 10.2147/AMEP.S302897. PMID: 33911913; PMCID: PMC8071692.

Everything They Don’t Tell You About Diabetes (But Should)

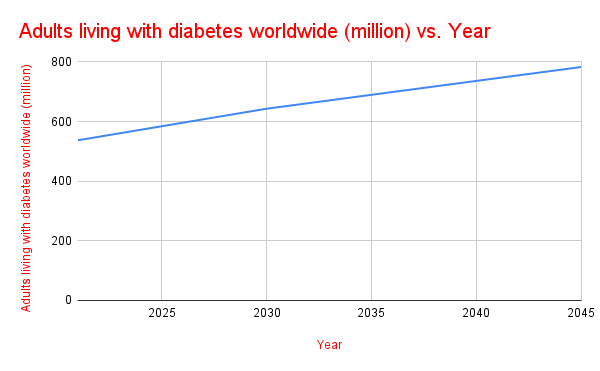
Over 537 million adults (20–79 years) were living with diabetes worldwide in 2021. That number is projected to rise to 643 million by 2030 and 783 million by 2045.

More adults are expected to be living with diabetes in 2045

Diabetes is one of the most common chronic conditions in the world today. It affects how your body turns food into energy. It happens when your blood sugar levels are too high because your body either doesn’t make enough insulin or can’t use it well. Insulin is a hormone that helps glucose from food get into your cells to be used for energy. When this process doesn’t work properly, sugar stays in your bloodstream. Over time, diabetes can lead to serious health issues.

What Is Diabetes?

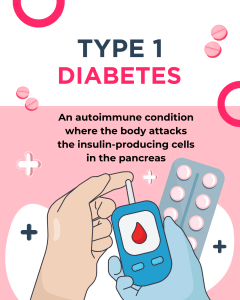
At its core, diabetes is a condition that affects how your body processes blood sugar (glucose). There are several types of diabetes. Type 1 diabetes is an autoimmune condition where the body attacks the insulin-producing cells in the pancreas. Type 2 diabetes, the most common type, happens when the body becomes resistant to insulin or doesn’t produce enough of it. Gestational diabetes occurs during pregnancy and usually goes away after childbirth, but it increases the risk of developing Type 2 diabetes later. Other,less common forms of diabetes can also occur due to genetic conditions, medications, or diseases of the pancreas.

Common Symptoms of Diabetes

Symptoms of diabetes can be subtle at first, especially with Type 2 diabetes. However, some early warning signs can help you catch it before complications arise. These include:

  • Frequent urination
  • Extreme thirst
  • Unexplained weight loss
  • Increased hunger

Other signs you might notice include darker patches of skin on the neck (a condition called acanthosis nigricans), recurring infections (especially urinary or skin), blurred vision, and even sexual dysfunction. Some people experience pain, tingling, or numbness in their hands or feet—this is a sign that diabetes may be affecting the nerves.

When Should You See a Doctor?

If you’re experiencing any of these symptoms—especially more than one—it’s a good idea to talk to a doctor. Even if you’re not showing obvious signs, routine screening is recommended if you’re over 45 or have risk factors such as being overweight, having a family history of diabetes, or living a sedentary lifestyle. Diabetes is diagnosed through blood tests like the A1C test, fasting blood sugar test, or an oral glucose tolerance test.

Understanding Risk Factors

Some risk factors for Type 2 diabetes are beyond your control, such as age, ethnicity, and family history. However, many risk factors are related to lifestyle, including physical inactivity, poor diet, high blood pressure, and excess weight—especially fat around the abdomen. Stress can also play a role, as chronic stress may raise blood sugar levels and make insulin resistance worse.

Living with Diabetes

Diabetes doesn’t just affect your blood sugar; it impacts nearly every part of your life. It can affect how you feel day to day, limit what you eat, and even cause emotional distress. But with the right knowledge and habits, many people with diabetes live long, active, and fulfilling lives. Managing diabetes means making smart food choices, staying physically active, monitoring your blood sugar levels, and sometimes taking medication or insulin.

Myths and Misconceptions

One of the most common myths is that eating too much sugar directly causes diabetes. While diet does play a role, it’s more about the overall pattern of eating, lifestyle, and genetics. Another myth is that only overweight people get diabetes—while weight is a risk factor, many people of normal weight also develop the condition. And no, diabetes is not contagious, and it can’t be cured with home remedies or “detoxes.”

Complications of Diabetes

If left untreated or poorly managed, diabetes can lead to serious complications. These include:

  • Heart disease
  • Kidney failure
  • Vision loss
  • Nerve damage
  • Limb amputations

The major problem with diabetes is not just high blood sugar, but the damage it can do quietly over time to major organs. This is why managing it well and catching it early is so important.

Prevention and Early Action

The good news is that Type 2 diabetes is often preventable. A healthy diet, regular physical activity, maintaining a healthy weight, and managing stress can go a long way in lowering your risk. If you’ve been told you have prediabetes—meaning your blood sugar is higher than normal but not high enough to be diabetes—it’s a sign to act now. Making small lifestyle changes can help you avoid full-blown diabetes and even reverse prediabetes.

Treating and Managing Diabetes

There’s no one-size-fits-all treatment, but diabetes can be managed effectively. This often involves a combination of medication, insulin (for some people), diet changes, and exercise. Some people can manage their diabetes without medication through lifestyle changes alone, especially if it’s caught early. Regular monitoring is key to staying in control.

Eating Right for Diabetes

A good diabetic diet focuses on whole foods like vegetables, lean proteins, whole grains, and healthy fats. Portion control and timing your meals can also help manage blood sugar levels. Foods to avoid or limit include sugary drinks, processed snacks, and refined carbohydrates. Working with a nutritionist can be incredibly helpful.

Stages and Progression

Diabetes doesn’t develop overnight. The four stages include insulin resistance, prediabetes, early Type 2 diabetes, and more advanced diabetes with complications. Knowing these stages can help you catch and manage the condition early, potentially avoiding the more serious effects altogether.

Conclusion

Diabetes is a serious condition, but it’s also manageable—and often preventable. With early detection, lifestyle changes, and the right medical support, you can take control of your health and live well. Don’t wait until symptoms become severe. If you’re at risk or experiencing signs, speak to a doctor. Your future self will thank you.


Can Bacteriophage Therapy Replace Antibiotics to Combat Bacterial Resistance?

Can Bacteriophage Therapy Replace Antibiotics to Combat Bacterial Resistance?

Key Points

  • Research suggests bacteriophages, viruses that kill bacteria, could help combat antibiotic resistance, a growing global health crisis.
  • It seems likely that phages won’t fully replace antibiotics but may complement them, especially for multidrug-resistant infections.
  • The evidence leans toward phages being effective in specific cases, like chronic infections, with some success stories in countries like Georgia and Poland.
  • There’s ongoing debate about regulatory hurdles and the need for more clinical trials to standardize phage therapy.

Can Bacteriophage Therapy Replace Antibiotics to Combat Bacterial Resistance?

Antibiotic resistance is a silent pandemic, with bacteria evolving to resist drugs, causing 133,000 direct deaths yearly in the European Region alone, and indirectly linked to 541,000 deaths annually, costing the EU/EEA €11.7 billion yearly in health and productivity losses.  1  This crisis threatens to undo medical progress, making infections like urinary tract infections potentially deadly.

Bacteriophages, or phages, are viruses that infect and destroy bacteria, offering a potential alternative. They’ve been used for over a century in some regions and are gaining attention as antibiotics fail against multidrug-resistant (MDR) bacteria, like those in the ESKAPE group (Enterococcus faecium, Staphylococcus aureus, Klebsiella pneumoniae, etc.).

ESKAPE species that have antibiotic resistance
ESKAPE species that are notorious for antibiotic resistance

ESKAPE pathogens are a group of highly drug-resistant bacteria that pose a significant threat to public health due to their ability to “escape” the effects of antibiotics. The term ESKAPE is an acronym for the six bacterial species in this group:

  • Enterococcus faecium
  • Staphylococcus aureus
  • Klebsiella pneumoniae
  • Acinetobacter baumannii
  • Pseudomonas aeruginosa
  • Enterobacter species

Why Are ESKAPE Pathogens Important?

  • They are major causes of hospital-acquired infections (HAIs).
  • They exhibit high antibiotic resistance, making infections difficult to treat.
  • They can cause severe illnesses, such as pneumonia, bloodstream infections, and urinary tract infections.
  • Some of them have biofilm-forming abilities, which makes them even harder to eradicate.

Due to their resistance mechanisms, these bacteria are a major focus in antimicrobial stewardship programs, and new antibiotic development efforts aim to combat them.

How Bacteriophages Work

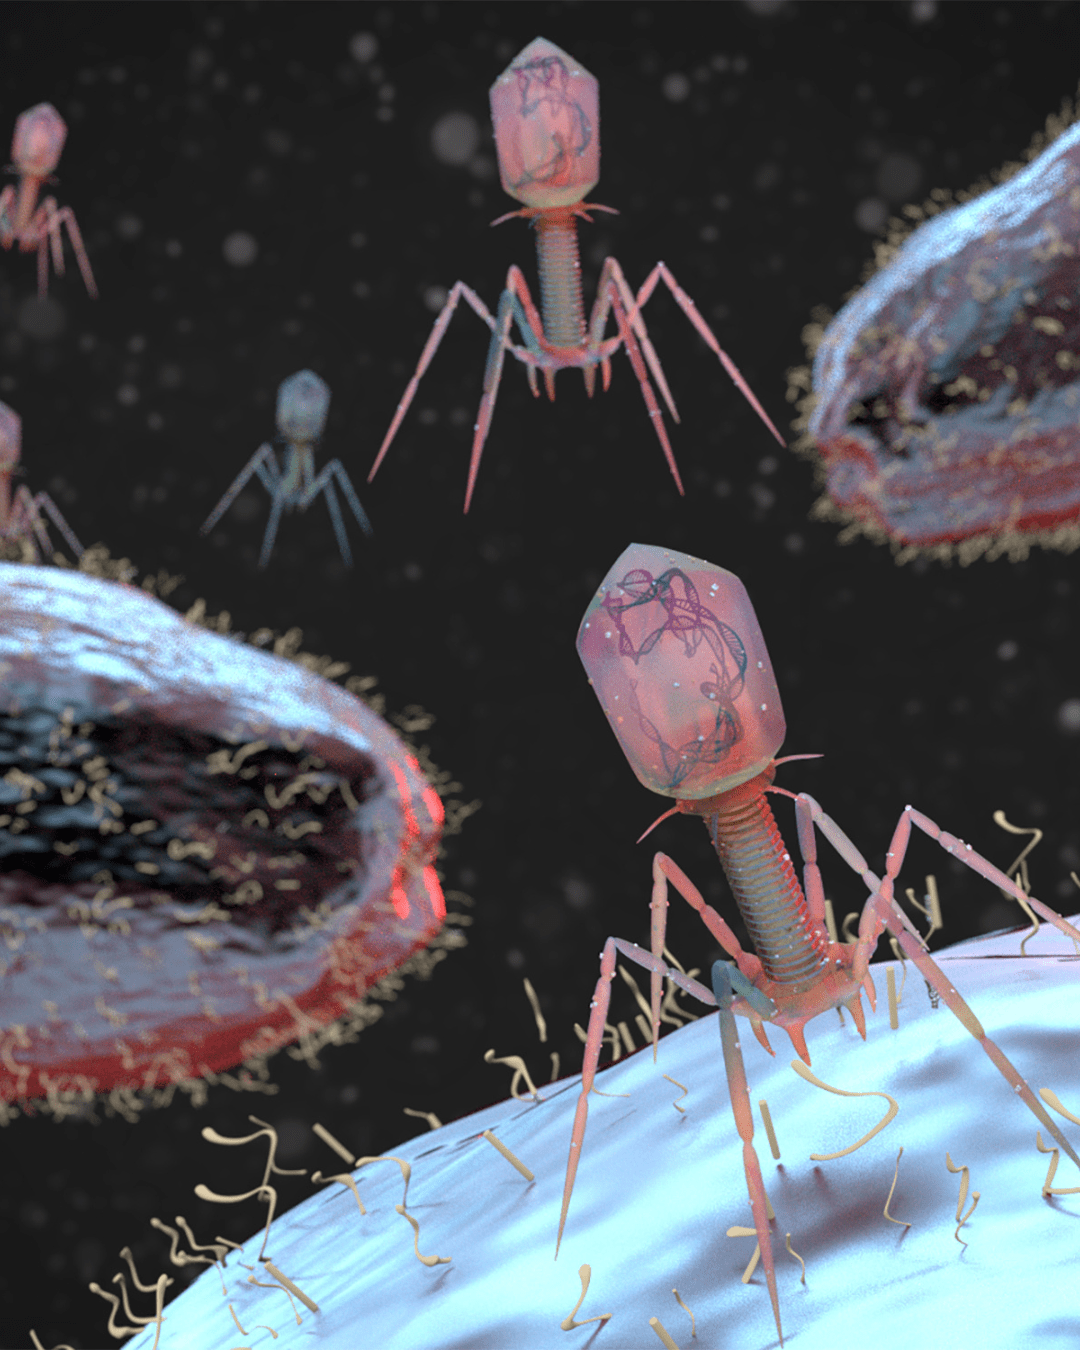
Phages attach to bacteria, inject their genetic material, and replicate inside, eventually bursting the cell to release more phages. With an estimated 10^30-31 phages in the biosphere, they’re highly abundant and specific, targeting only certain bacterial strains without harming human cells. This specificity could reduce side effects compared to broad-spectrum antibiotics.

Phages are the most abundant biological entities on Earth, with an estimated 10^30-31 in the biosphere, outnumbering bacterial cells by a factor of 10 (Principi et al., 2022). They operate by attaching to specific bacterial receptors, injecting their genetic material, and hijacking the bacterial machinery to produce progeny phages, ultimately lysing the cell. This lytic cycle ensures the destruction of the target bacterium, with phages being highly specific to certain strains, reducing the risk of disrupting the human microbiome (Górski et al., 2019).

This specificity contrasts with broad-spectrum antibiotics, which can kill beneficial bacteria and contribute to dysbiosis. Phages also self-replicate within the host, potentially providing a sustained therapeutic effect, and have low toxicity, with few reported side effects in clinical use (Górski et al., 2019).

Pharmacodynamics and Pharmacokinetics

Phage therapy relies on two approaches: active treatment, where low phage concentrations lead to progeny release, and passive treatment, using sufficient concentrations for immediate effect. The multiplicity of infection (MOI) and killing titer guide therapy, with low toxicity and no toxic by-products from immune degradation (Górski et al., 2019).

Pharmacokinetics are influenced by absorption, distribution, metabolism, excretion, decay, and proliferation. Routes include parenteral, oral, topical, and aerosolization, with examples like intraperitoneal injection being most effective in murine burn models for P. aeruginosa and oral dosing with 0.025% CaCO3 protecting phages from stomach acids (Górski et al., 2019).

Advantages Over Antibiotics

Phages offer several advantages, making them a compelling alternative:

  • High Specificity: For example, phage P100 infects over 90% of Listeria monocytogenes isolates, allowing precise targeting of pathogens (Górski et al., 2019).
  • Efficacy Against MDR Bacteria: Phages can treat infections caused by ESKAPE organisms, which are often resistant to multiple antibiotics (Lin et al., 2017).
  • Self-Replication: Phages multiply at the infection site, potentially reducing the need for high initial doses (Górski et al., 2019).
  • Low Toxicity: Clinical trials, such as a study on 26 patients receiving 10^9 PFU/kg, showed no antibody response in 8 cases and clearance within 4 days in 18 others, indicating good tolerance (Górski et al., 2019).
  • Biofilm Disruption: Phages can penetrate and disrupt bacterial biofilms, a common challenge in chronic infections, with engineered phages enhancing this capability (Lin et al., 2017).

Current Clinical Use and Case Studies

Phage therapy is actively practiced in countries like Russia, Georgia, and Poland, where it has been part of medical practice for decades. The Eliava Phage Therapy Centre in Georgia, for instance, has treated over 8,400 patients since 2018, emphasizing patient-centered, personalized care (World Health Organization, 2024). In Poland, the cure rate is close to 40%, based on historical data (Principi et al., 2022).

Notable case studies include:

  • Pim van Vliet: An 84-year-old with a chronic urinary tract infection caused by MDR Klebsiella pneumoniae, unresponsive to antibiotics. Starting phage therapy in May 2017 at the Eliava Institute, he recovered within a month and has remained infection-free, recently celebrating his 91st birthday (World Health Organization, 2024).
  • Marit: Suffering from chronic urethral infections due to MDR E. coli from age 3 to 11, Marit received phage therapy at Eliava in 2018. After a 14-day clinic treatment and six months at home, the bacteria were eradicated. Now 18, she is healthy, studying, and playing sports (World Health Organization, 2024).

Clinical trials also show promise: for example, a trial for burns treated 27 patients with a phage cocktail (10^6 PFU/mL), achieving a median endpoint of 144 hours compared to 47 hours with standard care (Górski et al., 2019). However, formal trials are limited, and access to Russian and Polish journals can be a barrier.

Challenges and Limitations

Despite the promise, several challenges persist:

  • Immune Response: Phages can trigger innate and adaptive immune responses, with variable antibody induction. High doses (10^9 PFU/mL) in mice showed increased IgG after 3–5 weeks and IgA after 63–79 days, while human trials showed no response in 8 of 26 patients and clearance within 4 days in 18 others (Górski et al., 2019). Low-dose regimes can mitigate neutralizing antibodies.
  • Bacterial Resistance to Phages: Up to 80% resistance in intestinal studies and 50% in sepsis models, mitigated by phage cocktails, genetic engineering, and exploiting fitness costs of resistant mutants (Górski et al., 2019).
  • Regulatory Hurdles: Phages lack specific classification, complicating trials and commercialization. Belgium defined them as medicinal/industrial products in 2016, and compassionate use is permitted under programs like the US FDA Expanded Access Program (Górski et al., 2019).
  • Standardization Needs: No standardized protocols for administration, dosing, or phage selection, with current collections like Finland’s ca. 600 phages estimated to need 1500–2000 to cover 70–80% of MDR isolates (Principi et al., 2022).
  • Access Barriers: Limited access to Eastern European journals and lack of integration into medical curricula hinder adoption (World Health Organization, 2024).

Future Prospects and Global Efforts

The future of phage therapy lies in combination with antibiotics, leveraging phage-antibiotic synergy, where antibiotics induce phage production by bacterial hosts (Kortright et al., 2022). Genetic engineering expands host ranges, with examples like T2 phage modified to infect E. coli O157:H7, and adds functionalities like CRISPR-Cas for sequence-specific antimicrobials (Górski et al., 2019).

The WHO is leading efforts to build evidence, with the Roadmap on AMR (2023–2030) targeting safer environments by 2030 (World Health Organization, 2024). This includes webinars, expert dialogues, and regulatory discussions from a One Health perspective, emphasizing human, animal, and environmental health. Educational needs, as highlighted by patients’ families like Lies (Pim’s daughter), call for health worker training and legislation to support early-stage use, preventing chronic suffering (World Health Organization, 2024).

Conclusion

Bacteriophages offer a promising, though not complete, replacement for antibiotics, particularly for MDR infections. While success stories like Pim and Marit illustrate potential, challenges like regulatory barriers and immune responses require resolution (World Health Organization, 2024). With global efforts and research, phage therapy could become a cornerstone of future medicine, addressing the silent pandemic of bacterial resistance.

Did you find this interesting? Leave a comment below.

References